Clean claims alone do not protect ASC revenue. That's the polite myth billing teams tell themselves right before a payer trims the line, packages the implant, or forces the center to chase underpayment for months. The core


Clean claims alone do not protect ASC revenue. That's the polite myth billing teams tell themselves right before a payer trims the line, packages the implant, or forces the center to chase underpayment for months. The core

A Type 2 NPI is the 10-digit National Provider Identifier assigned to a healthcare organization, not an individual provider. It's the identifier that sits on the billing side of the claim, so the payer knows which legal

CPT 90750 is the product code for the recombinant zoster vaccine, Shingrix, and it's billed per dose with an administration code such as 90471 plus diagnosis Z23. If a shingles claim is missing any one of those
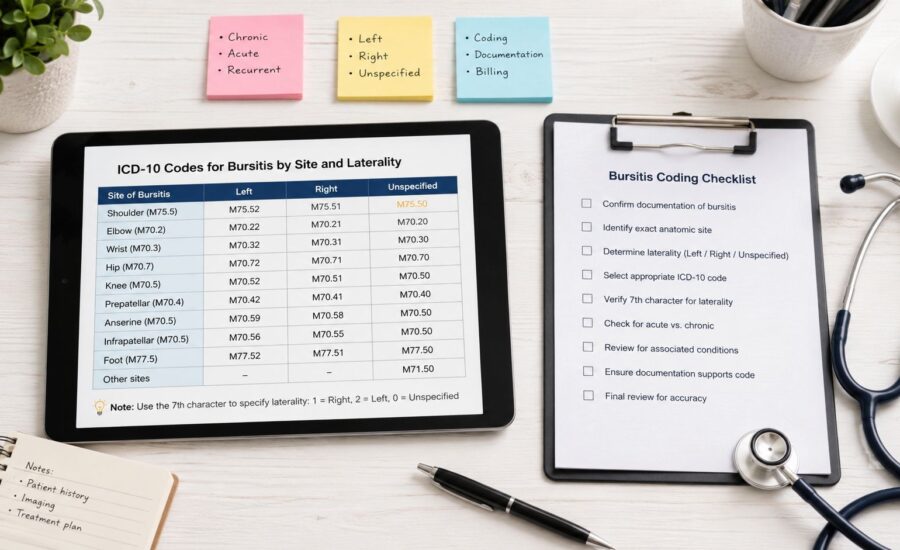
You're reviewing a chart that just says “bursitis,” the claim is waiting to go out, and the coder has to decide whether that one word is enough to survive payer edits. In practice, bursitis ICD 10 isn't

You're staring at a BCBS denial that should've been routine. The therapy note is signed, the codes look right, the patient showed up, and yet the claim is delayed, downcoded, or denied by an affiliate that seems

You're in the week that exposes every weak spot in GI billing. The endoscopy note says bleeding, the ED note says melena, the inpatient H&P says GI hemorrhage, and billing still needs one clean diagnosis line that

The charge nurse sees the chart first, then the silence in the hallway. A patient who was supposed to recover has suffered an unexpected permanent injury, and the team now has a sentinel event on its hands.

A Processor Control Number, or PCN, is a secondary routing number used by pharmacies to direct prescription drug claims to the correct processor, working alongside the BIN. If the PCN is wrong or missing, a claim can

Data from the National Association of Insurance Commissioners shows that 28% of dual-coverage claims are initially billed to the wrong payer due to automated eligibility errors. For a specialty practice, that isn't a front-end nuisance. It's a

A denial hits your work queue before coffee. The claim looked routine when it left the office. The procedure was performed, the note was signed, and the code selection seemed defensible. Then the payer asks for records,

