You're probably looking at a spreadsheet right now that tells you something is wrong, but not what to do next. Aging A/R is creeping up. Denials are eating staff time. One payer keeps paying late or light.

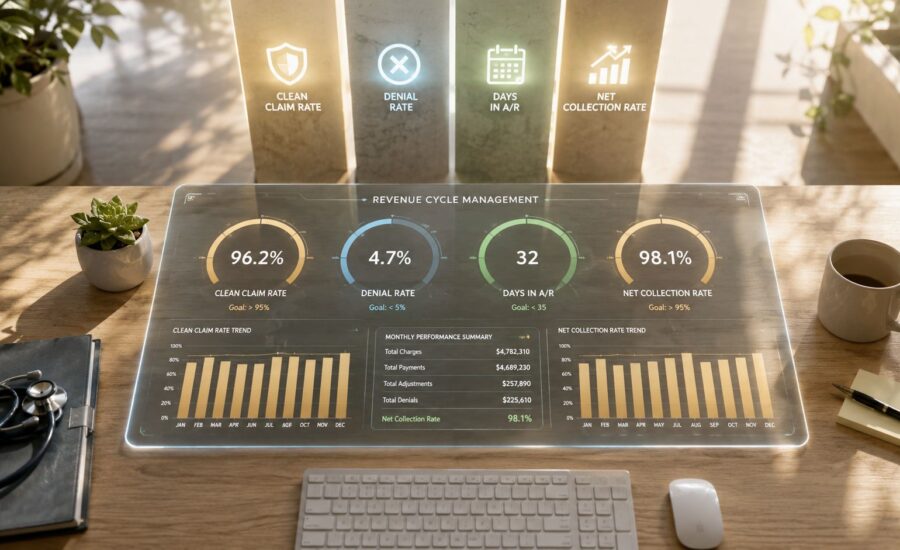
You're probably looking at a spreadsheet right now that tells you something is wrong, but not what to do next. Aging A/R is creeping up. Denials are eating staff time. One payer keeps paying late or light.

Administrative cost is not a side issue in healthcare. It is one of the clearest threats to margin, staffing stability, and cash flow. The American Hospital Association has reported that administrative functions account for more than 40%

Monday starts with a stack of eligibility issues from Friday, a payer portal that timed out halfway through claim status checks, and a coder asking whether the op note supports the modifier the surgeon documented. By noon,
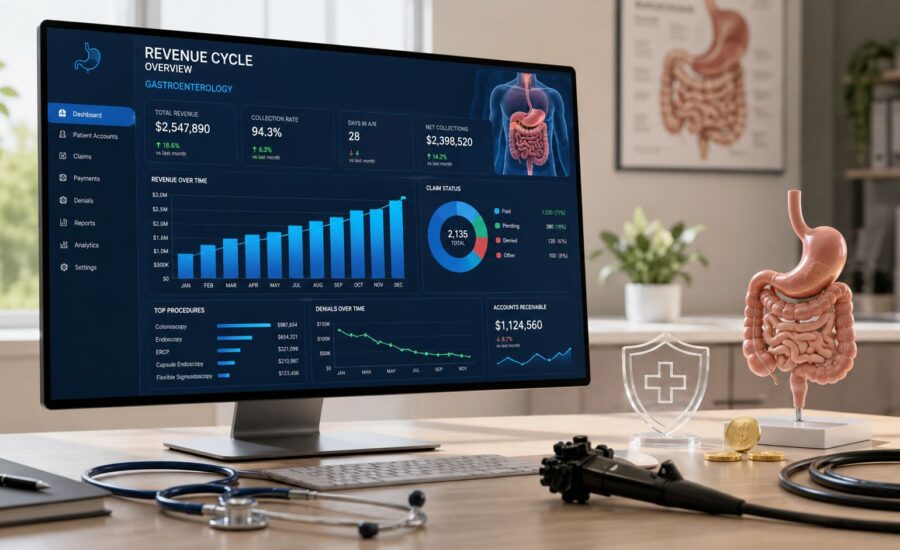
An 18% decline in professional reimbursement for gastroenterology services between 2018 and 2022, alongside an 11% drop in procedure frequency and a 7% drop in participating gastroenterologists, changes how a practice has to think about billing. This

If you own or lead a practice right now, you're probably balancing two jobs that don't fit neatly together. One is medicine. The other is protecting cash flow while staffing stays tight, payer behavior stays unpredictable, and

Payers do not need to deny a claim to reduce its value. They can approve it at the wrong rate, reprice it through payer-specific logic, downcode it, or apply contract terms the practice does not challenge. For

A payer just held a facility claim, your billing team says the coding looks fine, and cash you expected this month is now sitting in limbo. That's a familiar problem in hospitals, ASCs, rehab centers, and other

Denials used to be treated as friction. They now look more like a structural margin threat. In 2025, 41% of providers said at least 10% of their claims were denied, up from 38% in 2024 and 30%

You're probably staring at a queue of remits, patient statements waiting to go out, and aging balances that don't make sense. The payer says the claim processed. Your billing system says the encounter is still short. The

Monday starts with a familiar escalation. A patient had emergency care, your clinicians did the work, the claim went out clean, and the payer's response still doesn't match the service you delivered. Before the law changed, that

